
The Complex Colon Polyp: An Image and Video Atlas of Essential Concepts (66-min): Full Course lecture in Colon Polypectomy on EndoCollab by Klaus Mönkemüller.
Klaus Mönkemüller shows the colon polyps that make polypectomy hard, case by case, in photos and video. He sorts them with the EndoCollab classification: by shape, size, number, location, histology, earlier biopsy, and syndrome.
Guests can watch the first 13 minutes. Members get all 66 minutes, with chapters and a searchable transcript.
Continue with EndoCollab membership.
Get this lecture, the rest of this course, and the full EndoCollab library.
What you will learn
- The EndoCollab classification: shape, size, number, location, histology, iatrogenic, and syndromic polyps.
- Do not biopsy a polyp you think is resectable. Biopsies under-diagnose it and the fibrosis makes resection harder.
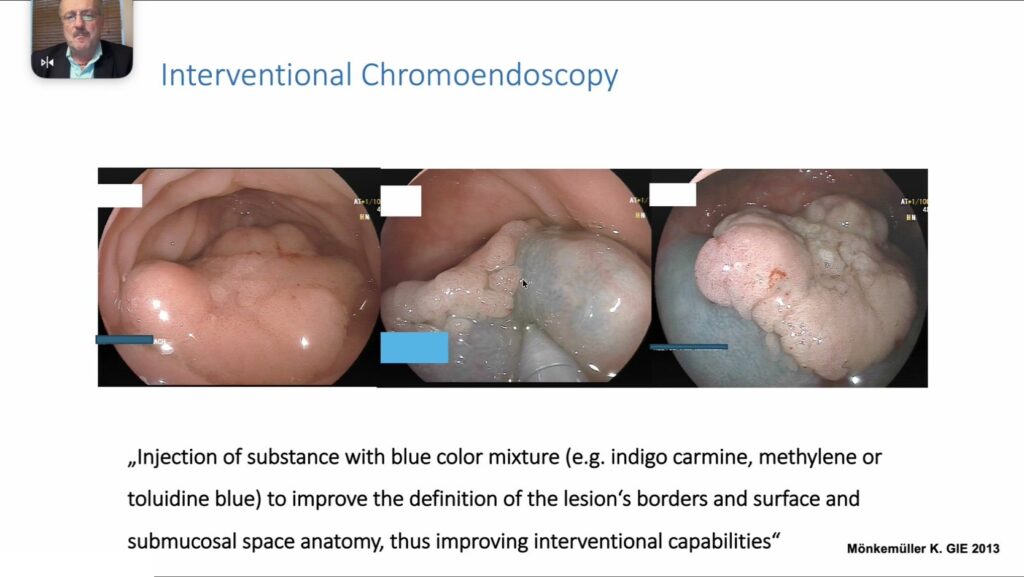
- Interventional chromoendoscopy: a blue submucosal cushion defines the borders and exposes flat archipelago-like lesions.
- Four-quadrant injection is a myth. One or two injections, even from in front of the polyp, can give a full cushion.
- Dynamic injection: the nurse pulses the syringe while you move the needle, the wheels, and the shaft.
- Snare pressure, strangulation, and water while cutting to disperse the current.
- Snare-tip circumferential incision, then the final snare: hybrid ESD-EMR for a lateral R0 margin.
- Thick stalks: endoloop or clips at the base, then cut at least 2 mm above the clips.
- The suction-mark trick so you never lose a small flat lesion again.
- The cecum, the anal verge, polyps between folds, inside a diverticulum, and a 5 cm lipoma.
- Lynch and Peutz-Jeghers: why a syndromic polyp is a complex polyp.
Inside the 66-minute lecture
38 chapters. The free preview runs to 13:14.
- 0:00Introduction and aimsFree preview
- 1:05The tiny polyp you see, then loseFree preview
- 1:58The EndoCollab classification for difficult colon polypsFree preview
- 2:57Do not biopsy a polyp you plan to resectFree preview
- 4:11Large polypsFree preview
- 4:54Bulky lesions: inject, then defineFree preview
- 6:03Laterally spreading lesions and chromoendoscopyFree preview
- 7:26The aim is R0 resectionFree preview
- 7:53The submucosal cushion and interventional chromoendoscopyFree preview
- 10:30Flat archipelago-like lesionsFree preview
- 11:36Snare orientation and the small defectFree preview
- 14:08Snare-tip incision for a lateral R0 marginMembers
- 16:17Four-quadrant injection is a mythMembers
- 18:40Injection solutions: mix it the color of the skyMembers
- 21:03Dynamic injection: the nurse and the endoscopistMembers
- 23:30Snare pressure and dynamic resectionMembers
- 24:52Snare-needle device and hybrid ESD-EMRMembers
- 28:48Laterally spreading tumors and piecemeal EMRMembers
- 30:51Depressed lesions and the pit patternMembers
- 32:33Non-granular flat lesions: when to markMembers
- 34:15Use water to tell left from rightMembers
- 34:45Lesions with a funny shape or baseMembers
- 36:17Proactive clip closureMembers
- 38:38Traction and countertractionMembers
- 39:39Thick stalks: endoloop and clipsMembers
- 44:50Small flat lesionsMembers
- 45:10The suction-mark trickMembers
- 46:32Multiple polypsMembers
- 47:12The cecum: injection and underwater EMRMembers
- 50:56Lesions found on retroflexionMembers
- 51:16Polyps hiding between foldsMembers
- 52:17On top of folds and at the anal vergeMembers
- 56:02Lipoma: enucleation with the snare tipMembers
- 57:23Diverticulum mimics and polyps inside a diverticulumMembers
- 59:24Iatrogenic polyps: after biopsy, and full-thickness resectionMembers
- 1:01:26Syndromic polyps: Lynch syndromeMembers
- 1:03:49Peutz-Jeghers syndromeMembers
- 1:05:11SummaryMembers
Continue with EndoCollab membership.
Get this lecture, the rest of this course, and the full EndoCollab library.
Course: Colon Polypectomy · Browse all lessons in Colon Polypectomy
Continue reading with a membership
Get access to the full content, course videos, case library, and our private WhatsApp community.
Already a member? Log in
We protect your privacy. No spam. Unsubscribe anytime.
