
Case Report
 Mohamed Hossny, MD; Klaus Mönkemüller, MD, PhD; Adil Mir, MD
Internal Medicine Residency and Department of Gastroenterology, Augusta Health, Fishersville, Virginia, USA; Department of Gastroenterology, Virginia Tech Carilion School of Medicine, Roanoke, Virginia, USA
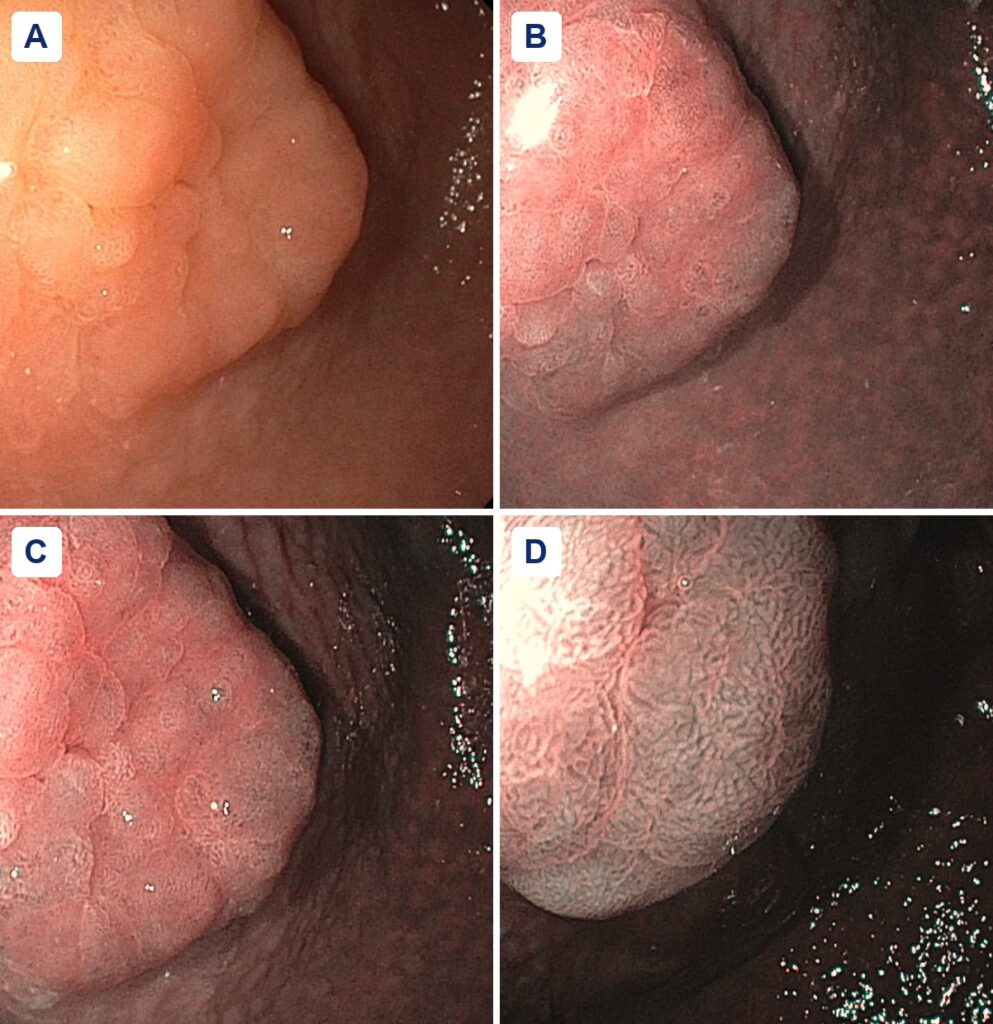
A 55-year-old woman underwent esophagogastroduodenoscopy for worsening gastroesophageal reflux symptoms. She had no known hereditary cancer or polyposis syndrome and no family history of colorectal cancer or advanced colorectal polyps. A raised gastric lesion was noted along the anterior wall of the stomach, near the incisura, 2 cm in size, with clearly demarcated borders, a pale-pink surface, rounded nodules, and shallow intervening grooves (Figure 1A). Narrow-band imaging (NBI) highlighted closely packed, curved and elongated surface lines, making the architectural contrast with the surrounding mucosa more conspicuous (Figure 1B–D). Biopsies were obtained which confirmed a gastric adenoma without dysplasia. Gastric biopsies were negative for Helicobacter pylori infection. This lesion was ultimately completely removed by endoscopic mucosal resection (EMR).
Figure 1 · Gastric adenoma before resection

Gastric adenomas are uncommon premalignant epithelial lesions, accounting for approximately 0.5–10% of gastric polyps in reported Western series.[1] They often occur in a background of gastric atrophy and intestinal metaplasia, although a hereditary syndrome is not required. Their importance lies in the risk of progression to adenocarcinoma and the possibility of carcinoma within an apparently innocuous polyp. Larger lesions, high-grade dysplasia, and villous architecture carry greater malignant risk.[1] Neither a bland color nor a smoothly lobulated contour reliably establishes the benign nature of the lesion; NBI assists characterization, but histology remains necessary for diagnosis and grading.[1,2]
A careful gastric examination is essential even when the indication is reflux. Clear mucus and pooled fluid, distend the lumen adequately, and inspect the stomach systematically in forward and retroflexed views, exposing mucosa hidden between folds. Any focal change in contour, color, or surface texture deserves closer examination. Use NBI to define the lesion’s borders and assess its surface; with magnification, evaluate the microsurface and microvascular patterns separately. An irregular pattern within a demarcated area should raise concern for early gastric cancer.[2] Record the lesion’s location, size, and morphology, and obtain white-light and NBI images. Inspect the remaining stomach for synchronous lesions and assess the background mucosa for atrophy, intestinal metaplasia, and Helicobacter pylori.[1,3]
EMR was used in this case; the choice of resection technique depends on lesion characteristics, with current guidance favoring endoscopic submucosal dissection for most superficial gastric neoplasia and EMR for selected small lesions. Bleeding and perforation are procedural risks, while residual or recurrent neoplasia requires follow-up informed by resection histology and background mucosal risk.[3] Recognition begins with the focal architectural change: an incidental gastric polyp warrants deliberate inspection before its significance is judged.
References
- Banks M, et al. British Society of Gastroenterology guidelines on the diagnosis and management of patients at risk of gastric adenocarcinoma. Gut. 2019;68:1545–1575. doi:10.1136/gutjnl-2018-318126.
- Yao K, et al. Guidelines for endoscopic diagnosis of early gastric cancer. Dig Endosc. 2020;32:663–698. doi:10.1111/den.13684.
- Dinis-Ribeiro M, et al. Management of epithelial precancerous conditions and early neoplasia of the stomach (MAPS III): ESGE/EHMSG/ESP Guideline update 2025. Endoscopy. 2025;57:504–554. doi:10.1055/a-2529-5025.
For your teaching file
Save this case as a PDF
Opens the companion page on The Practicing Endoscopist.
